
A diagnosis of von Hippel-Lindau (VHL) syndrome can raise many questions about the future, including whether having children is possible and what options are available for starting a family. While planning a family with VHL can involve additional decisions, many people with VHL go on to have healthy pregnancies and children.
Today’s reproductive medicine offers more choices than ever before. Whether you are considering natural conception, prenatal testing, Pre-implantation Genetic Testing for Monogenic Disorders (PGT-M), surrogacy, adoption or donor conception, there is no single “right” path to parenthood. The best choice is the one that feels right for you and your family.
This guide explains the main family planning options available to people affected by VHL, including pregnancy considerations, genetic testing and fertility treatment. Although this page focuses on VHL, many of the same principles also apply to other inherited cancer syndromes, including Hereditary Leiomyomatosis and Renal Cell Cancer (HLRCC/FH gene) and Birt-Hogg-Dubé syndrome (BHD/FLCN gene).
Please note: Every individual with VHL is different. The information on this page is intended as a general guide and should not replace advice from your clinical genetics team, fertility specialist or other healthcare professionals.
Quick links
Can I have children if I have VHL?
Pre-implantation Genetic Testing for Monogenic Disorders
Can I have children if I have VHL?
Yes. Many people with VHL go on to have healthy families.
VHL is an autosomal dominant genetic condition. This means that if one parent has VHL, each pregnancy has a 50% (1 in 2) chance of inheriting the altered VHL gene.
It is important to remember that VHL can affect people very differently. Even members of the same family who carry exactly the same genetic variant may experience different symptoms, tumour types and disease severity.
Understanding your options early can help you make informed decisions that are right for you and your family. Your clinical genetics team can explain your individual risk and discuss the reproductive options available.
Pregnancy and VHL
Many women with VHL have normal pregnancies and healthy babies.
Researchers have investigated whether pregnancy affects tumour growth in VHL, but the results have been mixed. Some studies have suggested that certain tumours may grow more quickly during pregnancy, while others have found little or no effect. At present, there is no clear evidence that pregnancy consistently accelerates VHL disease.
Because symptoms associated with VHL—such as headaches, vomiting and raised blood pressure—can also occur during pregnancy, careful monitoring by your obstetrician and specialist team is important.
Your doctors may recommend additional monitoring depending on your individual medical history, previous treatments and current tumour burden.
Family Planning Options
There is no single “right” way to build a family.
The options available include:
- Natural conception
- Natural conception with prenatal genetic testing
- Pre-implantation Genetic Testing for Monogenic Disorders (PGT-M)
- Surrogacy
- Egg or sperm donation
- Adoption
Your genetics team can help you understand the benefits, limitations and suitability of each option based on your personal circumstances.
Prenatal Testing
Couples who conceive naturally may choose prenatal testing to determine whether their baby has inherited the family’s VHL variant.
Chorionic Villus Sampling (CVS)
CVS is usually performed between 11 and 14 weeks of pregnancy.
A small sample of placental tissue is collected and analysed for the known VHL variant. Because the placenta and baby develop from the same fertilised egg, the result accurately indicates whether the baby has inherited VHL.
Further information:
https://www.nhs.uk/conditions/chorionic-villus-sampling-cvs
Amniocentesis
Amniocentesis is usually performed between 15 and 18 weeks of pregnancy.
A small sample of amniotic fluid containing fetal cells is collected and tested for the family’s known VHL variant.
The results of either test can help parents make informed decisions about the pregnancy.
Further information:
https://www.nhs.uk/conditions/amniocentesis
Pre-implantation Genetic Testing for Monogenic Disorders (PGT-M)
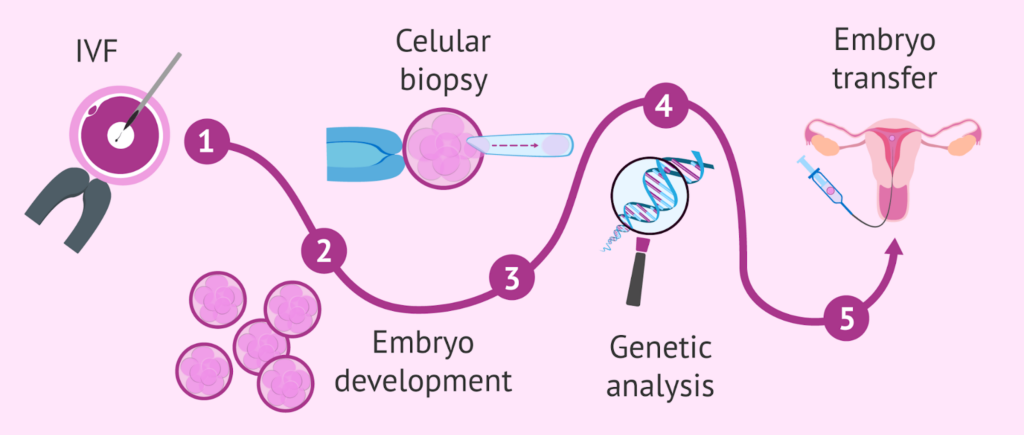
Pre-implantation Genetic Testing for Monogenic Disorders (PGT-M), previously known as Pre-implantation Genetic Diagnosis (PGD), is a fertility treatment that combines IVF with genetic testing to reduce the chance of passing on an inherited condition such as VHL.
Embryos are created through IVF (or IVF with ICSI where appropriate) and tested before pregnancy begins. Only embryos that have not inherited the family’s disease-causing variant are considered for transfer.
VHL is an approved condition for PGT-M in the UK (OMIM #193300), and many families affected by VHL have successfully had children using this treatment. HLRCC and BHD are also approved conditions.
Although PGT-M is well established, success cannot be guaranteed and some couples require more than one treatment cycle before achieving a pregnancy.
How does PGT-M work?
The treatment usually involves the following stages:
- Referral from your GP, Clinical Genetics Service or fertility specialist.
- Fertility assessment and treatment planning.
- Hormone medication to stimulate the ovaries.
- Egg collection.
- Fertilisation using IVF or Intracytoplasmic Sperm Injection (ICSI).
- Embryos are grown in the laboratory until the blastocyst stage.
- A small number of cells are carefully removed from each embryo (embryo biopsy).
- The cells are genetically analysed to identify which embryos have inherited the family’s known genetic variant.
- An unaffected embryo may be transferred into the uterus.
- If treatment is successful, the resulting child will not have inherited the VHL variant.
Many couples undergoing PGT-M do not have fertility problems. IVF is used because it allows embryos to be genetically tested before pregnancy.
Who is eligible for PGT-M?
Eligibility varies depending on where you live and whether treatment is funded privately or through the NHS.
Within the UK, VHL is an approved condition for PGT-M.
For NHS-funded treatment, eligibility commonly includes:
- Referral through an NHS Clinical Genetics Service.
- The female partner beginning treatment before the age of 40.
- Meeting local fertility funding criteria.
- Both partners being non-smokers.
- BMI within the accepted treatment range.
- No living unaffected biological child from the current relationship (under current NHS funding policies).
Funding criteria differ between England, Scotland, Wales and the Republic of Ireland, so your local genetics service or fertility clinic can advise what applies to your situation.
Important Information About Genetic Variants
For NHS-funded PGT-M, the identified genetic variant must be classified as either:
- Pathogenic, or
- Likely Pathogenic
Variants classified as Variants of Uncertain Significance (VUS) are not currently eligible for NHS-funded PGT-M because there is insufficient evidence that they are disease-causing.
If you are unsure how your family’s variant has been classified, your genetics team will be able to advise
Surrogacy
Surrogacy may be an option if pregnancy would pose significant health risks because of VHL or another medical condition.
However, many women with VHL are able to safely carry pregnancies themselves. Your specialist team can advise whether surrogacy is appropriate based on your individual circumstances.
Frequently Asked Questions
If I already have one child with VHL, is my next child more or less likely to inherit it?
Neither.
Each pregnancy is independent. Without PGT-M, every pregnancy has a 50% chance of inheriting VHL regardless of previous pregnancies or whether the baby is a boy or girl.
Is PGT-M available on the NHS?
It can be.
Funding depends on meeting national and local eligibility criteria. Your genetics team or fertility clinic will be able to explain what funding is available where you live
Does PGT-M work if the father has VHL?
Yes.
The parent carrying the VHL variant can be either the mother or the father. If the father has VHL, IVF and PGT-M can still be used to identify embryos that have not inherited the altered gene.
Do I have to choose PGT-M?
No.
There is no “correct” way to have a family.
Some people choose natural conception, some choose prenatal testing, some pursue PGT-M, while others choose surrogacy, donor eggs or sperm, adoption, or decide not to have children.
The right decision is the one that is right for you and your family.
Further Information
Human Fertilisation and Embryology Authority (HFEA)
General information:
https://www.hfea.gov.uk/
Approved PGT-M conditions:
https://www.hfea.gov.uk/treatments/embryo-testing-and-treatments-for-disease/approved-pgt-m-and-ptt-conditions/
PGT-M information:
https://www.hfea.gov.uk/treatments/embryo-testing-and-treatments-for-disease/
Find a licensed fertility clinic:
https://www.hfea.gov.uk/choose-a-clinic/
NHS
IVF:
https://www.nhs.uk/conditions/ivf/
Chorionic Villus Sampling (CVS):
https://www.nhs.uk/conditions/chorionic-villus-sampling-cvs/
Amniocentesis:
https://www.nhs.uk/conditions/amniocentesis/
Genetic Alliance UK
Pre-implantation Genetic Testing:
https://geneticalliance.org.uk/information/service-and-testing/how-can-i-access-preimplantation-genetic-diagnosis/
NHS Commissioning Policies
England
https://www.england.nhs.uk/wp-content/uploads/2014/04/e01-med-gen-0414.pdf
Scotland
Wales
Republic of Ireland
PGT-M has become increasingly available in Ireland in recent years. Availability may vary between clinics.
Examples of clinics offering PGT-M include:
Beacon Care Fertility:
https://www.beaconcarefertility.ie/treatments-services/reproductive-genetics/pre-implantation-genetic-testing-for-disease/
Merrion Fertility Clinic:
https://merrionfertility.ie/pre-implantation-genetic-testing/
These clinics are provided for information only and do not represent endorsement by VHL UK & Ireland.